Hermeneutic Medicine and Its Neighbors

Hermeneutic Medicine and Its Neighbors

Hermeneutic Medicine and Its Neighbors

Hermeneutic medicine treats the patient as a sacred text and the clinical encounter as a sacred space of interpretation. A critical reading of my forthcoming monograph by Arthur Kleinman identified three linked deficits: reliance on his early work rather than his later moral and ontological turn; clinical vignettes too thin to carry the theory built on them, in which patients and families nearly disappear; and isolation from medical anthropology, the anthropology of morality, the history of science, and cultural psychiatry. This article accepts the critique and maps the neighborhood. It reads Kleinman's later work (What Really Matters, The Soul of Care, A Passion for Society, The Practice of Wisdom), Byron Good's explicitly hermeneutic Medicine, Rationality and Experience, Cheryl Mattingly's narrative phenomenology and first-person virtue ethics, the ordinary-ethics tradition of Veena Das, Michael Lambek and Jarrett Zigon, Annemarie Mol's praxiography of the body and of care, and Laurence Kirmayer's cultural psychiatry together with the DSM-5 Cultural Formulation Interview. For each, I state where hermeneutic medicine agrees, where it differs, and what it must change. The central conclusion is that the textual metaphor survives only if it is rebuilt as a shared, polyphonic and enacted reading, closer to the study partnership (ḥavruta) and the many-voiced Talmudic page than to a solitary reader bent over a silent text. It then sets out a protocol for rebuilding the book's clinical cases and tests the author's own published papers against the same neighbors and criticisms, separating differences that are commitments from those that are defects.
Divine Concealment and the Clinical Limits of Theodicy

Divine Concealment and the Clinical Limits of Theodicy

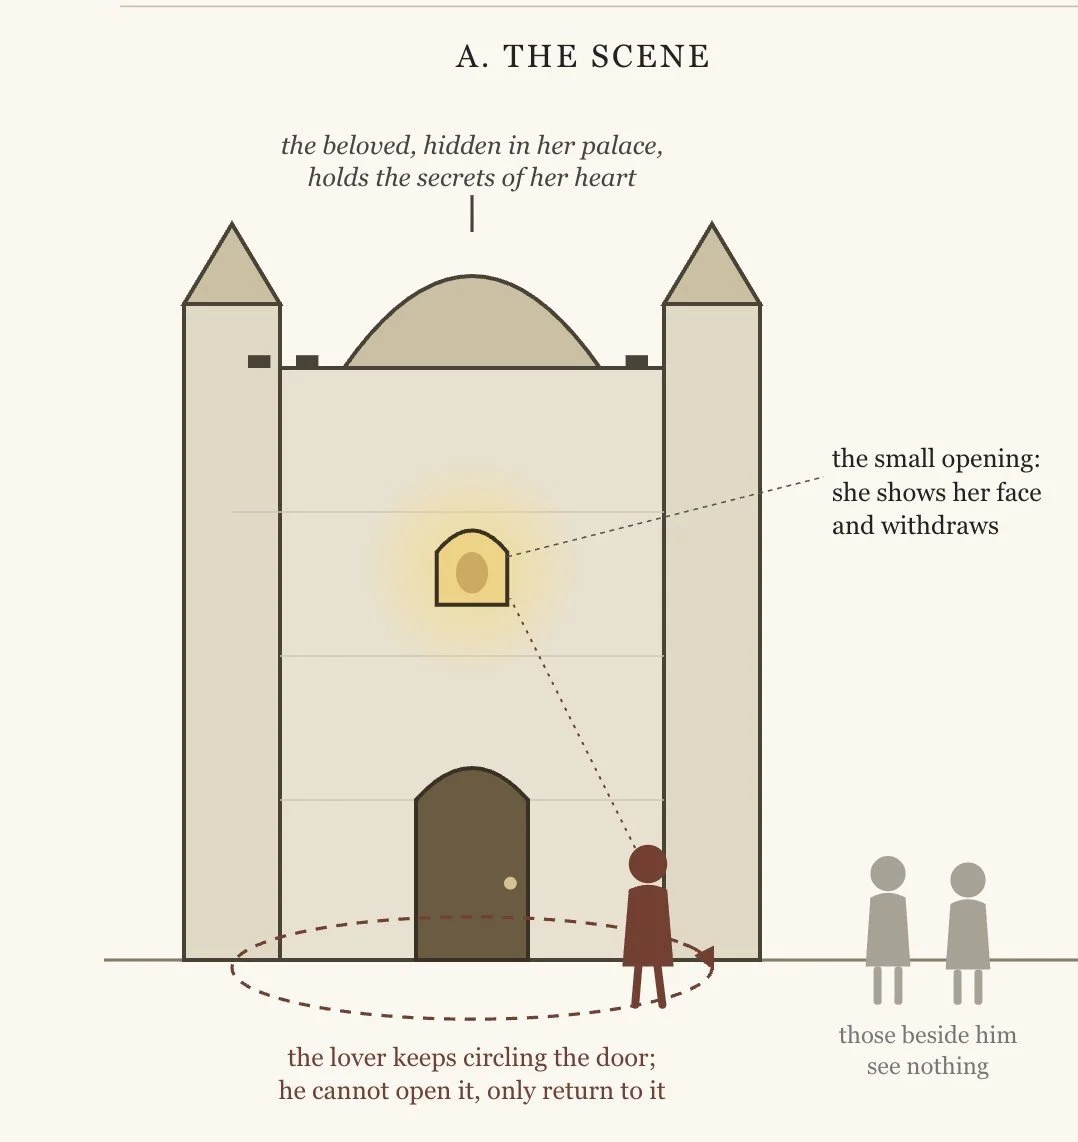
Patients facing catastrophic illness often ask a question medicine cannot answer: not how this happened, but why it happened to them. Two familiar responses fail. The first resolves the question by supplying a providential meaning; the second abandons it by treating the question as outside clinical scope. This essay proposes a third posture, holding the resolution: the clinician neither supplies nor forecloses a final meaning, but keeps open the possibility that one exists while refusing any authority to declare it. The argument is developed through a close reading of the beloved-maiden parable in the Zohar’s Sava de-Mishpatim (Zohar II 99a–b), read against a selected trajectory in the author’s published clinical theology, from concealed presence toward anti-theodicy, irreducible antinomy, and faithful nonsurrender. Four features of the passage carry the argument. Disclosure belongs to the beloved and is never seized by the lover. Knowledge of the stranger’s soul comes through one’s own estrangement rather than penetration of the other. The old man refuses to close his discourse when his listeners declare themselves satisfied. Most important, the culmination of face-to-face disclosure returns the lover to the plain sense of the text, to which nothing may be added and from which nothing may be taken away. From these features the essay derives four bedside disciplines and a criterion, the peshat test: any meaning offered at the bedside must leave the patient’s own words standing unaltered. The proposal does not suspend causal inquiry, treatment, or accountability for error, and it makes no empirical claim of efficacy. It offers a normative account of what a clinician may claim about the meaning of another person’s suffering, and of what remains owed when that meaning is withheld.

Reading the Network

Reading the Network

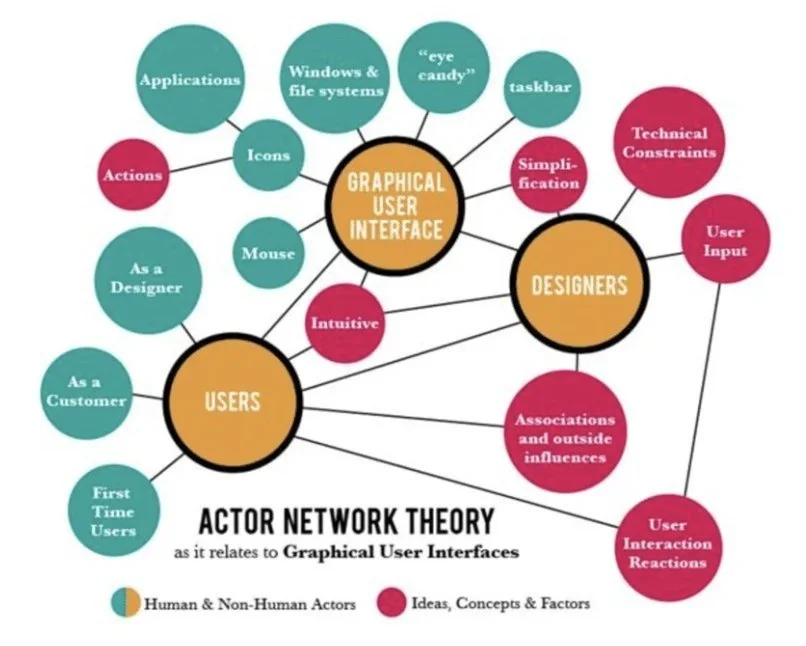
Much harm in contemporary medicine is done by networks that are competent at every node. A hospice agency, fourteen specialists, a discharge protocol and a diagnostic algorithm can each be correct on their own terms and still carry a patient toward the wrong outcome. This paper argues that Bruno Latour's actor-network theory (ANT) gives clinicians a precise vocabulary for seeing how this happens, and that a rabbinic reading discipline, which I call scientific midrash, gives them a method for undoing it.

The argument proceeds through eight cases from five decades of neurological practice, drawn from the manuscript The Broken Vessel: Hermeneutic Medicine and the Sacred Work of Healing. Each case is traced as a network: its inscriptions (charts, printouts, files), its scripts (templates, reimbursement rules, rooms), its chains of translation (referrals) and its crossings between what Latour calls modes of existence (reference, religion, organization, law). In each, the decisive reading lay outside the layer that standard care was reading. In seven cases the re-reading reduced intervention; in one it rightly demanded more.

Three contributions follow. First, Latour's own origins in biblical exegesis, where truth is kept by a disciplined chain of transformations rather than by resemblance, show that midrash and ANT share a theory of fidelity. Second, the rabbinic rule that a verse never leaves its plain sense (ein mikra yotze midei peshuto) functions as a clinical analogue of Latour's circulating reference and keeps interpretation from overriding evidence. Third, the Jewish concept of shleimut (wholeness) supplies the normative criterion that ANT, by design, withholds: it lets a clinician judge which assemblies of humans and non-humans heal and which harm.

Trust Before Knowing, Humility After

Trust Before Knowing, Humility After

A single typed page from a manuscript argues that knowledge is safe only when it is enclosed by two forms of trust: a faith that precedes knowing and a deeper faith that follows it. Written as a Hasidic homily on the Noah narrative, the discourse describes the epistemic and moral structure of the clinical encounter with unusual precision. Drawing on fifty years of neurological practice, I read it alongside the literature on diagnostic error, physician burnout, defensive medicine, dementia care, prognostic communication, and therapeutic restraint. I argue that its three-part structure (trust before knowledge, rigorous knowledge, humility after knowledge) gives clinicians a vocabulary for failures our technical language can name but not repair: premature closure, depersonalization, defensive practice, reductionism, and the inability to stop. I close with concrete implications for clinical teaching and answer three objections, including the charge that religious language has no place in clinical reasoning.

The Hunger Beyond Naming

The Hunger Beyond Naming

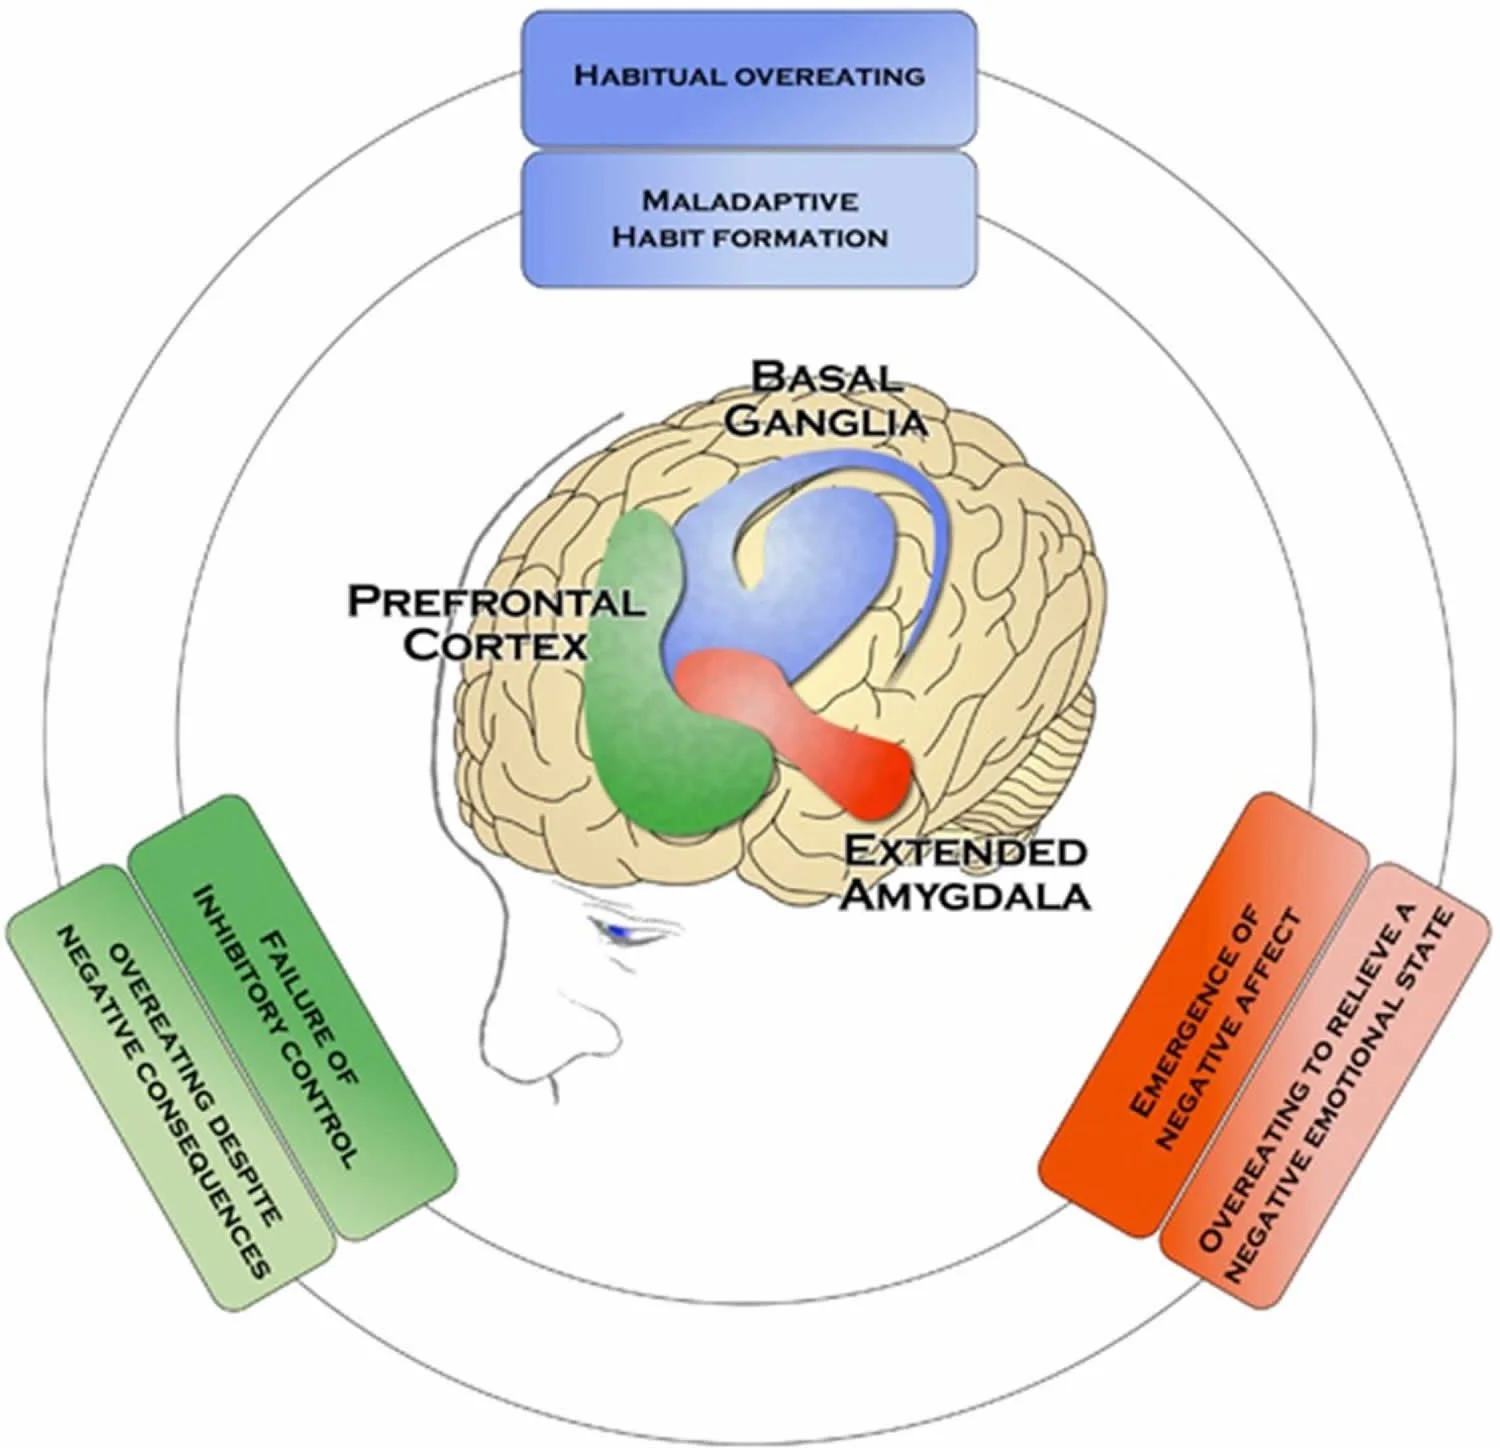
Compulsive eating is increasingly described in the language of addiction, yet the construct remains contested. Most people with obesity do not meet food-addiction criteria, and many who do are not obese. This paper proposes that three vocabularies rarely brought together describe the same clinical phenomenon from complementary sides: the neurobiology of reward, the practical theology of the Twelve Steps, and the classical tradition of apophatic, or negative, theology.

The neurobiological literature shows how the gap between desire and satisfaction is exploited. It documents the dissociation of incentive "wanting" from hedonic "liking," striatal dopaminergic adaptation, the recruitment of stress systems in negative reinforcement, interoceptive confusion, and the reward-maximizing design of ultra-processed foods. Glucagon-like peptide-1 (GLP-1) receptor agonists can now quiet craving, but clinical experience suggests that patients are often left facing an unfamiliar silence that pharmacology cannot interpret.

The paper argues that compulsive eating is best understood as a disorder of closure: a compulsion to close the gap between desire and satisfaction. Apophatic theology is, by contrast, a discipline of the gap kept open. Drawing on Pseudo-Dionysius, Maimonides, Gregory of Nyssa's doctrine of unending desire, Wolfson's critique of theomania, and the Lurianic concept of tzimtzum, the Twelve Steps are read as an applied apophatic practice. Step One functions as an unsaying of the self; the formula "God as we understood Him" is a deliberate refusal to fix the divine in a concept; and recovery transforms desire rather than abolishing it.

A mapping of the Steps onto theological, neurobiological, and clinical registers is offered as a set of testable hypotheses rather than established mechanisms. Clinical cautions are addressed, including the risk that rigid abstinence models pose to patients with eating disorders, weight stigma, and the uneven evidence base for Overeaters Anonymous. The paper closes with practical recommendations for the consulting room.

The Faustian Clinic

The Faustian Clinic

Goethe's Faust is usually read as a drama of knowledge, desire, transgression and redemption. It is also, and not incidentally, a drama about a physician. Faust has studied medicine along with philosophy, law and theology; he and his father treated plague victims with a remedy that killed more than it cured; and his despair begins not in appetite but in the discovery that accumulated knowledge has failed to yield wisdom or presence. His response is escalation rather than renunciation, and the wager he strikes with Mephistopheles is, precisely, a wager never to linger never to say to any moment, stay. This essay argues that the same wager is struck, quietly and repeatedly, by contemporary physicians, first with technique and then with the institutions that house it. Medicine rightly seeks knowledge, cure, prediction and control. It becomes Faustian when these instrumental goods harden into an anthropology: when disease becomes more real than the sufferer, uncertainty an intolerable defect, death a technical failure, and the physician able to remain in the room only while something remains to be done. The essay reads Mephistopheles as a grammar of reduction without return, Gretchen as the person left behind by the project, Philemon and Baucis as those who stand in the way of the system's throughput, and Sorge (Care) as the return of what mastery cannot eliminate. It places Goethe in conversation with Cassell on suffering, Buber and Levinas on the second person, the Book of Job and the rabbinic dying of Moses, and the author's earlier proposals of a "third grammar" for the clinical encounter, the detachability of remedy from cosmology, and clinical tzimtzum. The argument is not anti-technological. The corrective to Faustian medicine is neither therapeutic defeatism nor romantic anti-science but a disciplined self-limitation: knowing vigorously without claiming omniscience, intervening powerfully without confusing power with sovereignty, and remaining with the patient when neither explanation nor cure is available.

The Note and the Interval

The Note and the Interval

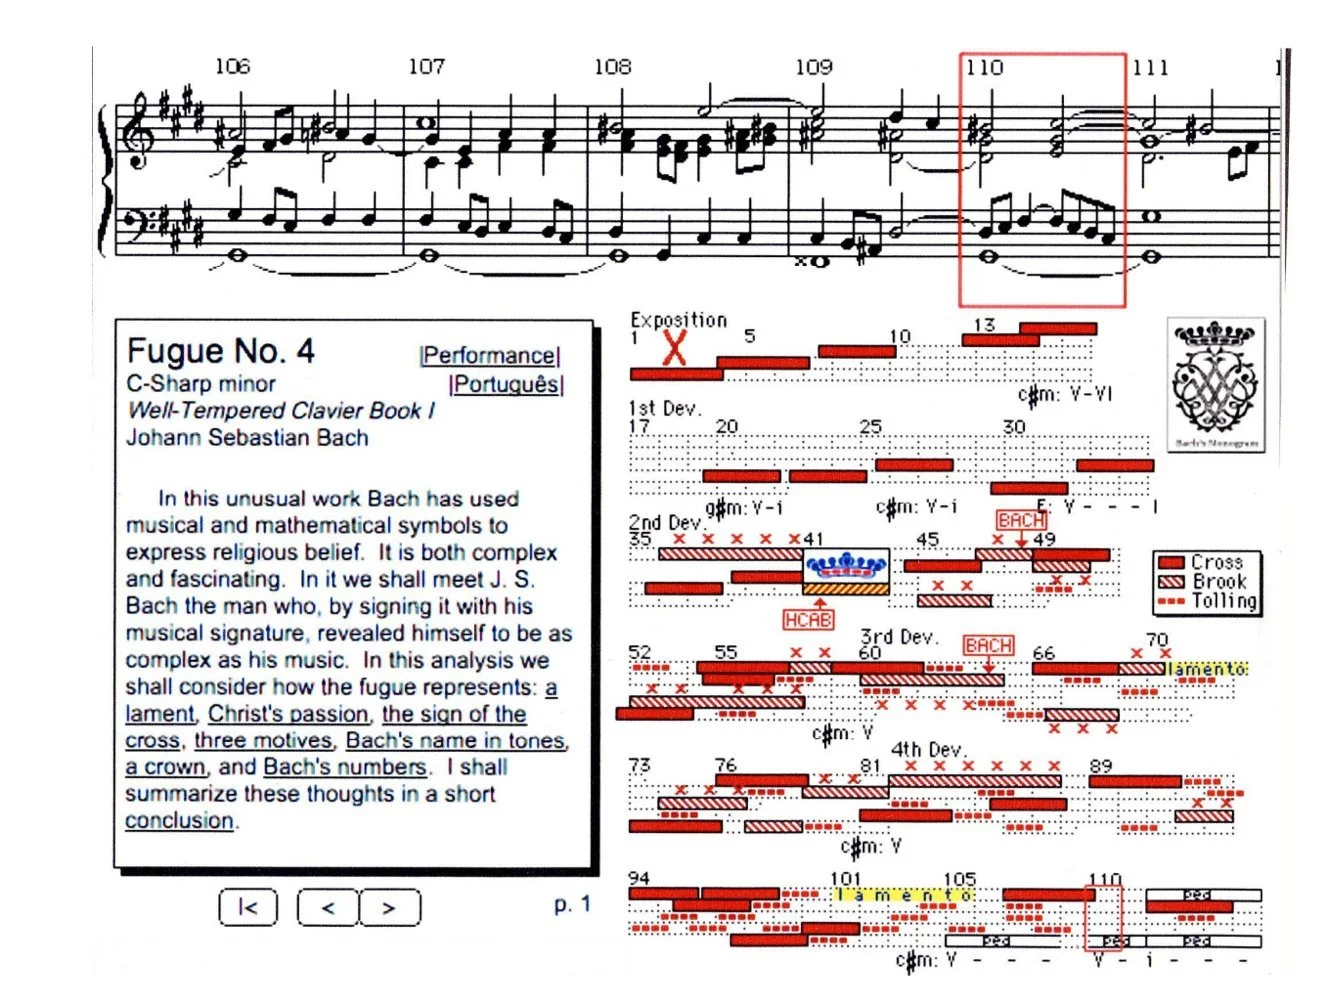
I have previously argued that the patient should be approached as a sacred text and the clinical encounter as an interpretive rather than an extractive act. That model has served and I do not abandon it. But a text can be read in silence, alone, at leisure, by someone who was not present when it was written, and none of those conditions holds at the bedside. This paper shifts the governing analogy one register: from text to score, from reading to hearing, from interpretation to performance. It draws on the neuropsychology of musical appreciation — the predictive architecture of expectation and the dopaminergic economy of anticipated resolution — on Iain McGilchrist’s account of two modes of attention, on the turn in musicology from work to performance (Goehr, Cook, Small, Zuckerkandl), and on Lawrence Kramer’s hermeneutics of music, whose triad of address, understanding and performance and whose concept of the hermeneutic window I take over directly. Four theses follow.

First, the patient’s presentation is not a finished text but an underdetermined score, which does not exist until it is performed.

Second, clinical meaning is carried in intervals rather than in notes, which also yields a physiological account of premature closure: unresolved expectation is aversive to a predictive reward system.

Third, the clinician stands inside the ensemble rather than outside the page, converting diagnostic authority into an ethics of accompaniment and redefining hermeneutic violence as the imposition of a cadence.

Fourth, and decisively, the analogy must be truncated at one point: the score has no composer.

Illness was not written and refusing that last step is what keeps a musical hermeneutics from collapsing into the aestheticization of suffering, which is theodicy in a beautiful coat. I set out the correspondences, offer a rehearsal discipline of six trainable listening habits, and answer the principal objections. The claim is not that medicine resembles music, but that both are arts of the temporal, the underdetermined and the unresolved, and that medicine has borrowed its self-understanding from the wrong one of the two.

The Capacity to Return

The Capacity to Return

Geroscience has converted aging from a chronological given into a set of measurable and potentially modifiable biological processes. The hallmarks of aging, methylation clocks, proteomic organ clocks, and cell-type-specific aging signatures now allow biological age to be estimated independently of the calendar. Two problems accompany this achievement. The first is epistemological: a measurable biomarker can quietly become the definition of the state it was built to estimate. The second is economic: longevity science is maturing inside a commercial ecosystem that rewards patentable molecules, proprietary assays, repeat testing, and the conversion of ordinary aging into a treatable anxiety.

Objective. To propose a clinical framework for longevity that integrates contemporary geroscience with the geriatric traditions of intrinsic capacity and physical resilience, and that names, with appropriate precision, the way commercial incentives shape which questions about aging become scientifically visible.

Discussion. I propose the term commercial epistemic distortion for the structural condition in which economic incentives influence which questions are funded, which endpoints are privileged, how results are disseminated, and which interventions achieve clinical prominence. The term is deliberately narrower than fraud and does not imply that industry-sponsored science is invalid. Against this background I propose Adaptive Longevity Medicine (ALM), whose central construct is adaptive coherence: the capacity of a person, understood as an integrated biological, psychological, and relational system, to absorb perturbation, coordinate a compensatory response, recover toward a prior or viable functional state, and preserve meaningful agency over time. ALM shifts the primary clinical measurement from state to recovery kinetics — what happens to the organism after it is disturbed, how fast it returns, how completely, and whether its systems return together. Nine domains are described, together with a four-level, deliberately non-proprietary Adaptive Coherence Profile and a falsifiable four-phase research program.

Conclusion. Healthy longevity is not a younger biomarker profile. It is the retained capacity to recover, function, relate, and pursue what one values. The organizing question of longevity medicine should therefore move from How old is this organism biologically? to When life disturbs the system, how much of this person comes back?

Fracture Within Mercy

Fracture Within Mercy

Clinical teaching holds that limits express care — that declining the late call or ending the visit is a mature form of the disposition that makes a good physician. This paper argues that the claim is structurally false, that its falsity is costly, and that a body of eighteenth-century kabbalistic reasoning states the correct account more precisely than anything in the clinical literature. In Jonathan Eibeschütz's Wa-Avo ha-Yom el ha-Ayin, analysed by Elliot Wolfson, judgment cannot be derived from unbounded lovingkindness by ordinary causation, since an effect resembles its cause and one may not posit opposites in a simple subject; it must therefore be spoken of as yesh me-ayin, something from nothing. The same source holds that the catastrophic breaking of the vessels occurs within Attiqa, a configuration characterised as entirely merciful, precisely because no judgment was present to impose restraint — unbounded efflux with no vessel being, in his phrase, seed spilled in vain. This yields a structural account of physician burnout that inverts the depletion model and is consistent with evidence that organisation-directed interventions outperform individual resilience training and that sustainable clinical closeness is differentiated rather than boundless. I set out the kabbalistic argument at length, including its transmission through the Chabad reading on which therapeutic applications have rested, and then state in detail where the position departs from my own previous publications on therapeutic ṣimṣum, self-kenosis, and sacred listening — including one direct reversal, since that earlier work prescribed further self-emptying as the remedy for burnout. Three theses result: limit is created rather than derived and must be taught as a distinct competence; the vessel that renders giving receivable is largely institutional; and the boundary is not the price of therapeutic space but its constitution.

“And so, it goes with God”

“And so, it goes with God”

Yann Martel's Life of Pi ends with a survivor offering two irreconcilable accounts of the same 227 days and asking his investigators not which is true but which they prefer (1). This paper takes that scene as the best available model of a situation clinicians meet constantly and are poorly trained to recognise: the patient who has more than one account, both their own, mutually untranslatable, and who is watching to see which one the room will accept. Two decades of criticism on the novel have divided sharply over whether its refusal to adjudicate is a philosophical achievement or a sleight of hand, and I survey that division because its terms are exactly the terms of the clinical problem. I then argue that the interpretive tradition best equipped to handle a text that is undecidable in reference while remaining determinate in use is the midrashic one, and that the rabbinic mashal — as analysed by Stern, Boyarin, Fishbane, and Kermode — supplies the structural category that the narrative-medicine vocabulary of "the patient's story" lacks. The mashal supplies an application and then withholds its sufficiency, leaving a residue the application fails to collect. Martel performs precisely this: he hands the reader the key, through the investigators' own decoding, and the first story does not collapse. Four consequences for practice follow — that the addressee participates in producing the version, that accounts are maintained at cost, that anomalous detail signals the account's limit rather than its falsity, and that institutional documents systematically require the version that helps patients least. Two symmetrical clinical errors are named, four criteria of discernment proposed, and the limit case examined, where no account can be constructed at all. Throughout, I distinguish three questions clinical training conflates — the etiological, the theodicy, and the endurance question — and argue that the patient's account answers the third while clinicians grade it as an answer to the first.